
- A tight, ropy band in a muscle with a tender spot that reproduces your pain when pressed, sometimes with a twitch or referred pain into the head, shoulder or buttock
- Neck and upper-back muscle pain (most often the trapezius and levator scapulae) from posture, desk work or after whiplash
- Low back or gluteal muscle pain that persists after the disc, facet or SI joint has been treated
- Pain that has not settled with 4–6 weeks of stretching, heat, massage, physical therapy or a muscle relaxant
- Tension-type headache traced to trigger points in the neck and shoulders
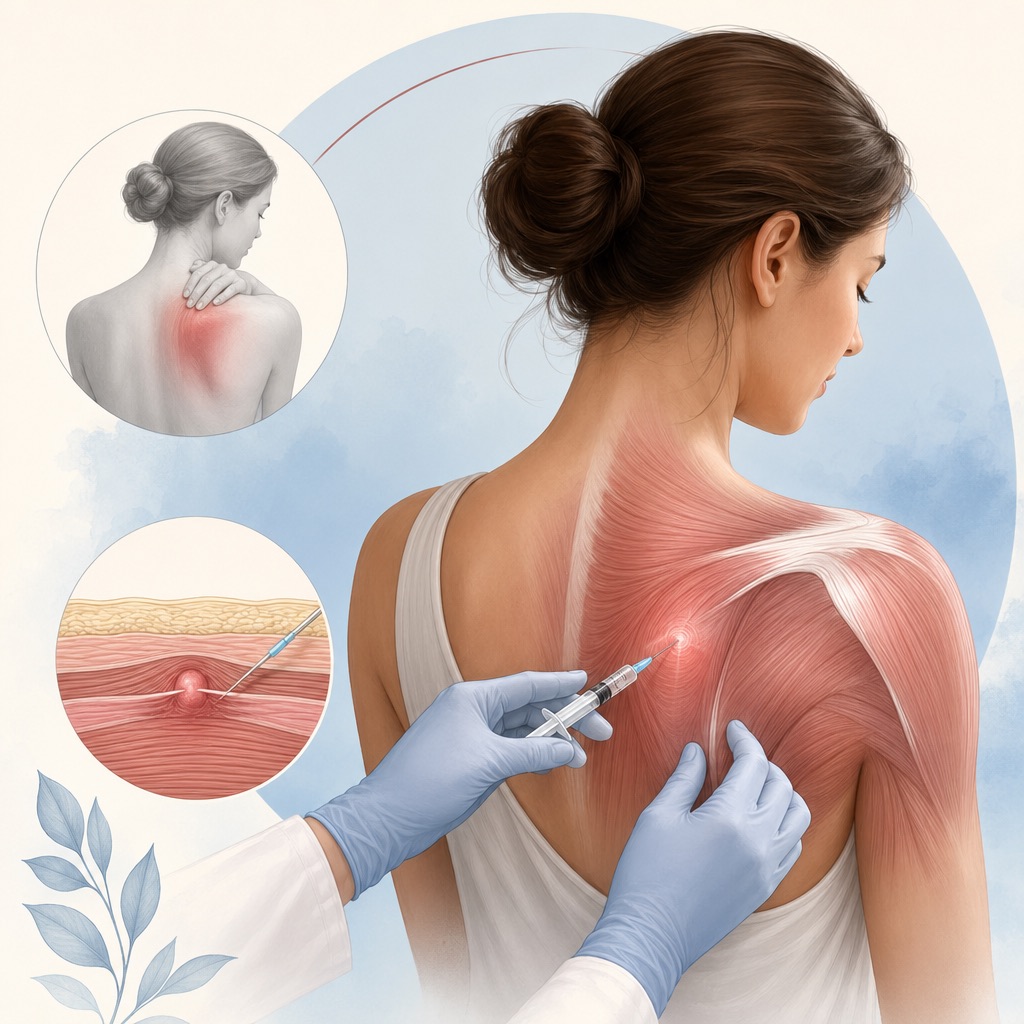
Joint & soft tissue
Trigger Point Injections
Trigger point injections in Houston: a 10-minute office procedure for painful muscle knots in the neck, shoulders and back. What to expect, limits, risks.
In short
A trigger point injection treats a tight, tender knot in a muscle (a myofascial trigger point) by placing a small amount of local anesthetic, sometimes with steroid, directly into it with a thin needle. It is a treatment, not a test, and one of the simplest procedures in pain medicine: about 10 minutes at an office visit, no imaging, often done the same day as your consultation. Relief typically lasts days to weeks and is meant to break a muscle spasm cycle so stretching and strengthening can take over. It is not a treatment for widespread pain such as fibromyalgia.
Key facts
| Treats | Myofascial pain from trigger points in the trapezius, neck, shoulder blade, low back, gluteal and hip muscles; muscle pain after whiplash or overuse; tension-type headache from neck trigger points |
|---|---|
| Test or treatment? | Treatment. It settles a painful muscle knot; it does not diagnose a joint, disc or nerve problem |
| Procedure time | About 10 minutes for 1–4 trigger points, at a regular office visit |
| Anesthesia | None needed beyond the injected local anesthetic; no sedation |
| Downtime | None; soreness for 1–2 days, then normal activity and stretching |
| When relief starts | Often within minutes from the anesthetic, with the muscle releasing over 1–3 days |
| How long relief lasts | Days to weeks; longer when combined with stretching, posture correction and strengthening |
| How often it can be repeated | Typically no more than once every 2 months at the same site, and no more than a few sessions per year; insurers require documented improvement to continue |
| Insurance | Covered by Medicare and most plans for documented trigger points after conservative care, with limits on frequency |
Who it is for
- Widespread pain in many areas with fatigue and poor sleep, the pattern of fibromyalgia; trigger point injections do not help widespread pain and can make it flare
- Pain that is actually coming from a joint, disc or nerve; the injection relieves muscle spasm that is a symptom, not the source, and we treat the source
- Skin infection over the muscle, or a bleeding disorder that cannot be managed
- Severe needle phobia or inability to sit still for the procedure
- Patients who have had several sessions without lasting benefit; repeating an ineffective treatment is not useful
How a trigger point injection works
A trigger point is a small patch of muscle fibers stuck in contraction. It feels like a firm knot in a tight band, is tender to press, and often sends pain elsewhere: trapezius trigger points refer pain to the temple and behind the eye, gluteal trigger points into the buttock and thigh. The stuck fibers have poor blood flow, which keeps them irritated, and the irritation keeps them contracted.
The injection breaks that loop mechanically and chemically. A thin needle is passed into the knot, often producing a brief local twitch as the fibers release, and a small amount of local anesthetic (lidocaine or bupivacaine, 0.5–2 mL) is injected. The needle itself does much of the work; studies comparing anesthetic injection with "dry needling" (the same needle, no medication) find similar relief, though the anesthetic makes the procedure more comfortable and reduces post-injection soreness. Steroid is sometimes added for a stubborn or inflamed point, but it adds little in most trials and can thin the tissue if repeated, so we use it sparingly.
No imaging is needed. The physician finds the trigger point by hand, and that exam is the whole diagnosis. You do not need to bring MRI or X-ray reports for this procedure, and you do not need a separate procedure-day appointment: trigger point injections are usually done at the visit where they are recommended. We perform them at our Houston and Webster offices, and in Pearland when that office opens in November 2026.
What happens at the visit
- Exam: the physician presses along the painful muscle to find each trigger point (the tender knot in a tight band that reproduces your pain) and marks it. Usually 1–4 points are treated per session.
- Positioning: sitting or lying so the muscle is relaxed; for trapezius and upper-back points, lying face down or on your side is used so a faint reaction does not lead to a fall.
- Skin preparation: the skin is cleaned with alcohol or antiseptic. No numbing injection is needed; the needle is thin.
- Injection: the physician pinches the muscle between two fingers to lift it away from what lies beneath, inserts the needle into the knot at a shallow angle, and injects a small amount of anesthetic while moving the needle tip through the band. A brief twitch or a reproduction of your usual referred pain is common and is a sign the right spot was found.
- Pressure and bandage: firm pressure for a minute to limit bruising, then a small bandage. The whole procedure takes about 10 minutes.
- Home: you may drive yourself. Stretch the treated muscle gently the same day; that is part of the treatment.
After the procedure
Day 0. The area may feel numb or oddly loose for an hour or two from the anesthetic. Gentle range-of-motion stretching of the treated muscle that day helps the release hold. Heat or ice, whichever you prefer, for 15 minutes at a time.
Days 1–2. Soreness or bruising at the injection sites is expected and is often described as feeling like a hard workout. It settles on its own; acetaminophen or an anti-inflammatory helps. Avoid heavy use of the muscle, but keep stretching.
Week 1–2. Relief from the muscle release is established. This is the window to work on the reason the trigger point formed: posture, workstation setup, sleep position, stress, or weakness of the muscles around it. Physical therapy, a home stretching program and, for neck and shoulder points, attention to desk ergonomics are what make the relief last; see physical therapy and home exercise.
Judging the response. A good response is relief of days to weeks with easier stretching. If the same point keeps returning within a week or two despite exercise, or if you have had 2–3 sessions without lasting benefit, we stop injecting and look again at whether a joint, disc or nerve is driving the muscle spasm.
Call us for shortness of breath or sharp chest pain after an injection in the trapezius, shoulder blade or rib-cage area, which could indicate a punctured lung and needs same-day evaluation, or for fever, spreading redness or drainage at the site.
What the evidence shows
Trigger point injections have been used for decades and are supported by many small trials and clinical experience, though the quality of the research is modest. Three findings are consistent. First, needling the trigger point is what matters: systematic reviews (Cummings and White and others) found that injecting local anesthetic, saline or nothing at all (dry needling) produced similar relief, which means the needle's disruption of the contracted fibers is the active ingredient and the anesthetic mainly improves comfort. Second, adding steroid does not improve results over anesthetic alone in most studies. Third, relief is usually short unless the injection is paired with stretching, strengthening and correction of the cause; injections alone rarely produce lasting change.
For fibromyalgia, the picture is different. The tender points of fibromyalgia are not trigger points, injecting them does not help, and the American College of Rheumatology's approach to fibromyalgia centers on exercise, sleep, education and specific medications rather than injections. We say so plainly because it prevents a common disappointment.
Medicare and most commercial insurers cover trigger point injections when trigger points are documented on exam and conservative care has been tried, and they limit frequency (typically a session no more often than every 2 months per site and a few sessions per year) with continued coverage tied to documented improvement.
Alternatives and what comes next
Stretching, heat, massage, physical therapy and a short course of a muscle relaxant treat most trigger points without a needle, and dry needling by a physical therapist is an equivalent alternative for patients who prefer to avoid medication. When trigger points keep returning in the neck and shoulders, the driver is often a cervical facet joint or nerve root; medial branch blocks or a cervical epidural steroid injection address those. Recurrent gluteal or low-back trigger points often sit on top of SI joint or facet pain. For headache from neck and scalp trigger points, an occipital nerve block is sometimes the better match. Persistent, widespread muscle pain is evaluated as a whole rather than point by point; see fibromyalgia and chronic pain.
Safety and preparation
- Blood thinners: trigger point injections are low bleeding-risk procedures and most patients continue aspirin and other blood thinners; expect more bruising. Tell us what you take; a hold is rarely needed and is arranged with your prescriber. Never stop a blood thinner on your own.
- Diabetes: if steroid is added, blood sugar can rise for 1–3 days; anesthetic-only injections do not affect glucose. Tell us if you are diabetic and we will usually omit steroid.
- Infection or fever: we reschedule for fever or a skin problem over the muscle.
- Allergies (contrast, steroid, local anesthetic): tell us about reactions to lidocaine, bupivacaine, dental numbing or cortisone. No contrast is used.
- Pregnancy: no X-ray is involved and the procedure can be done during pregnancy with anesthetic only; tell us so we omit steroid.
- Sedation and driving: no sedation is used and you can drive yourself home.
- Lung disease: tell us if you have emphysema, COPD or a prior collapsed lung, since injections near the rib cage carry a small pneumothorax risk that is higher with overinflated lungs.
- Imaging: none is needed for this procedure; you do not need to bring MRI or X-ray reports unless we are also evaluating a joint or nerve problem.
Risks and side effects
- Soreness at the injection sites for 1–2 days, like a hard workout
- Bruising
- A brief twitch or reproduction of your referred pain during the injection
- Temporary numbness or a loose feeling in the muscle for an hour or two
- Light-headedness or a vasovagal reaction, more likely when sitting up for neck injections
- A temporary flare of muscle pain for a few days
- Skin dimpling, lightening or fat loss at the site if steroid is used repeatedly
- Bleeding into the muscle in patients on blood thinners
- Allergic reaction to local anesthetic
- No lasting benefit
- Pneumothorax (punctured lung) from injections in the trapezius, shoulder blade, rib-cage or upper-back muscles, where the lung lies a short distance beneath; prevented by pinching the muscle away from the chest wall and angling the needle along it rather than toward the ribs. Shortness of breath or sharp chest pain after an injection needs same-day evaluation
- Infection at the site or an abscess in the muscle
- Nerve injury with persistent numbness or weakness, avoided by knowing the anatomy of each muscle
- Local anesthetic toxicity if a large total dose is used across many points (we limit the number of points per session)
Frequently asked questions
How long do trigger point injections last?
Typically days to weeks. The injection releases the muscle knot; stretching, posture correction and strengthening keep it released. Patients who pair the injection with a home program get the longest relief; patients who rely on injections alone usually see the point return.
Do trigger point injections hurt?
The needle is thin and no separate numbing injection is needed. Most people feel a sharp pinch and then a brief deep ache or twitch as the needle enters the knot, which lasts a few seconds. The area is sore for 1–2 days afterward, like after a hard workout.
Is a trigger point injection the same as dry needling?
Nearly. Dry needling uses the same needle technique without injecting medication and is often done by physical therapists. Studies show similar relief; the anesthetic in a trigger point injection makes the procedure more comfortable and reduces soreness afterward. Steroid is sometimes added but adds little in most trials.
Can I get trigger point injections at my first appointment?
Usually yes. The procedure takes about 10 minutes, needs no imaging or special preparation, and can be done at the visit where it is recommended if the exam confirms trigger points and it fits the plan.
How many trigger point injections can I have?
Insurers typically cover a session no more often than every 2 months at the same site and a few sessions per year, with continued coverage tied to documented improvement. Clinically, if two or three sessions have not produced lasting benefit, we stop and look for the underlying cause rather than continuing.
Do trigger point injections help fibromyalgia?
No. Fibromyalgia produces widespread tenderness rather than discrete muscle knots, and injecting tender points does not help and can trigger a flare. Fibromyalgia is treated with exercise, sleep management, education and specific medications, and we do not use trigger point injections for it.
Why did my doctor mention a collapsed lung?
Because the trapezius, shoulder blade and upper-back muscles sit a short distance above the lung, and a needle angled toward the ribs can puncture it. We prevent this by pinching the muscle away from the chest wall and angling the needle along the muscle rather than into it. The risk is small; the warning to report shortness of breath or chest pain after an injection is standard.
Sources
- Needling therapies in the management of myofascial trigger point pain: a systematic review (Cummings TM, White AR, 2001) (opens in new tab) — Archives of Physical Medicine and Rehabilitation
- Trigger Point Injections: Local Coverage Determination (opens in new tab) — Centers for Medicare & Medicaid Services (Medicare Coverage Database)
- Fibromyalgia: patient information and treatment approach (opens in new tab) — American College of Rheumatology
- Pneumothorax after trigger point injection: case reports and prevention (opens in new tab) — PubMed (case literature)
Next step
Request an appointment
Call (832) 916-2075 or request an appointment online. New patients are welcome; the team confirms insurance and referral requirements before scheduling.