
- Moderate-to-severe knee osteoarthritis (typically Kellgren-Lawrence grade 2–4 on X-ray) with pain for 3 months or more despite exercise, weight management, medication or injections
- Not ready for knee replacement, or not a candidate because of age, weight, heart or lung disease, or other medical risk
- Persistent knee pain 6 months or more after a total knee replacement, once the surgeon has excluded infection, loosening, instability or malalignment
- Patients who want to know whether genicular radiofrequency ablation is likely to help before committing to it
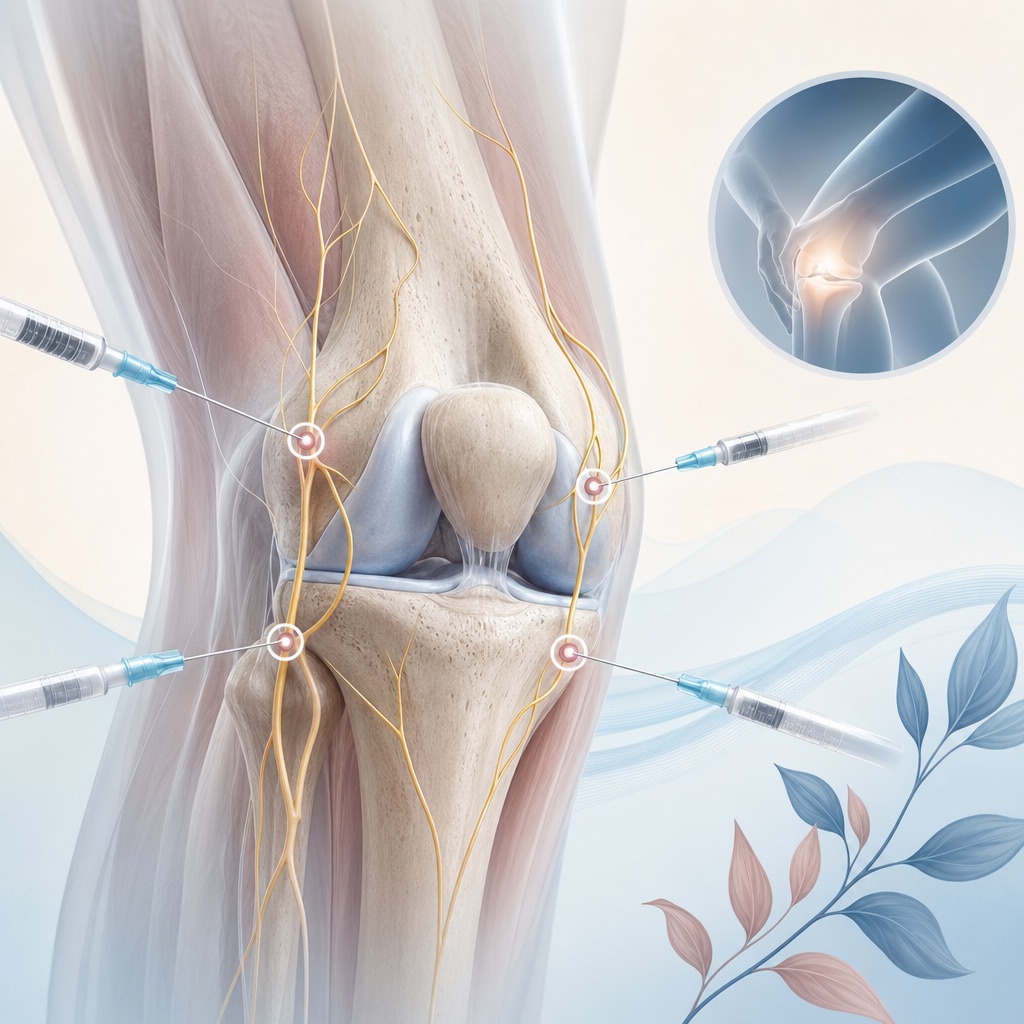
Diagnostic nerve block
Genicular Nerve Block (Diagnostic Knee Block)
Genicular nerve block in Houston: a diagnostic test that numbs three knee nerves for a few hours to predict whether genicular RFA will relieve knee pain.
In short
A genicular nerve block is a test, not a treatment. Under X-ray or ultrasound guidance, a small dose of local anesthetic is placed on three sensory nerves around the knee (the superomedial, superolateral and inferomedial genicular nerves). If your usual knee pain drops by at least half for the next few hours, those nerves carry the pain and you are a candidate for genicular radiofrequency ablation, which can quiet them for 6–12 months. Relief from the block itself is meant to last hours, not weeks.
Key facts
| Tests for | Knee pain from osteoarthritis, or pain that persists after a knee replacement, that might respond to genicular radiofrequency ablation |
|---|---|
| Test or treatment? | A test. It contains no steroid and is not expected to give lasting relief |
| Procedure time | 10–15 minutes; about 45–60 minutes at the office |
| Anesthesia | Local anesthetic in the skin only; no sedation, so your pain rating is reliable |
| Downtime | None beyond the day; most people walk out and return to normal activity the same day |
| When relief starts | Within 15–30 minutes |
| How long relief lasts | 1–2 hours with lidocaine, 4–8 hours with bupivacaine; then the pain returns, as expected |
| How often it is done | Once, or twice if your insurer requires two confirmatory blocks; a positive block (at least 50% relief) leads to ablation |
| Insurance | Covered by Medicare and most plans as the diagnostic step before genicular ablation; some plans require two blocks |
Who it is for
- Knee pain from a meniscal tear, ligament injury or other mechanical problem that surgery would fix; the block does not address these
- A hot, swollen, red knee, fever, or any concern for joint infection or gout, which need urgent evaluation
- Pain after knee replacement that has not yet been reviewed by the surgeon
- Patients who cannot reliably rate their pain over the next several hours
- Skin infection over the knee, a bleeding disorder, or blood thinners that cannot be managed
- Pregnancy, if fluoroscopy is used (ultrasound guidance is an alternative)
How a genicular nerve block works
The knee's sensation is carried by a group of small nerves called the genicular nerves that wrap around the ends of the femur and tibia. Three of them run at predictable spots against bone: the superomedial genicular nerve (inner side, above the knee), the superolateral genicular nerve (outer side, above the knee) and the inferomedial genicular nerve (inner side, below the knee). A fourth, the inferolateral nerve, is deliberately left alone because it runs close to the common peroneal nerve, which lifts the foot.
In knee osteoarthritis, pain signals from the worn joint travel through these nerves. Numbing them with about 1–2 mL of local anesthetic at each site does not treat the arthritis; it temporarily switches off the signal. If your usual pain, including pain with standing and walking, drops by at least 50% during the anesthetic window and then returns, the nerves are confirmed as the pathway and genicular radiofrequency ablation of the same three nerves has a good chance of giving 6–12 months of relief. If the block does little, ablation is unlikely to work and we look at other options.
The block is done under fluoroscopy (X-ray), which shows the bony landmarks where each nerve crosses, or under ultrasound, which shows the small artery that runs with each nerve. Both are accurate; ultrasound avoids radiation and is useful in pregnancy or when the knee contains metal from a replacement.
Who this test is for
Knee arthritis, not ready or not eligible for replacement. This is the largest group. Some patients are too young for a replacement that will wear out, some are waiting for a surgery date, and some cannot safely have surgery because of heart, lung, kidney or weight-related risk. Genicular ablation gives these patients months of relief at a time without affecting a future replacement.
Pain after total knee replacement. Around 1 in 5 people still have meaningful knee pain a year after replacement. Once the surgeon has ruled out infection, loosening, instability and malalignment, the remaining pain is often carried by the same genicular nerves, and ablation is one of the few options that does not involve another operation. The block and ablation are done at the skin and bone surfaces away from the implant.
Not a fit. Pain from a torn meniscus or ligament, a hot swollen joint, or a replacement that is loose or infected needs a different answer first.
What happens on procedure day
- Check-in: we record your baseline knee pain (0–10) at rest and with walking, confirm blood-thinner and allergy details, and hand you a pain diary. Take your usual medications but no extra pain medication that morning.
- Positioning: you lie on your back with a roll under the knee. The skin around the knee is cleaned and draped. No sedation is used.
- Numbing: a small amount of lidocaine in the skin at three points, two above the knee and one below on the inner side.
- Needle placement: under X-ray (or ultrasound), a thin needle is guided to the bone at each of the three genicular nerve targets, where the shaft of the femur or tibia meets the flared end. Position is confirmed in two views.
- Injection: 1–2 mL of local anesthetic at each site. The whole injection phase takes a few minutes.
- Testing: after 15–30 minutes we ask you to stand, walk the hallway, and climb a step if that normally hurts, and record your pain. You then go home (driving yourself is usually fine) and keep rating pain hourly for 6 hours.
After the block
First 6 hours. This is the test window. Walk, stand and do the activities that usually hurt, and rate your pain every hour on the diary. Note the time the pain returns. Avoid extra pain medication during this window unless you must (and write it down).
That evening. Expect your usual knee pain to be back. Mild soreness or bruising at the three needle sites for 1–2 days is normal; ice helps.
Next 1–3 weeks. We review the diary. At least 50% relief during the anesthetic window is a positive result and we request authorization for genicular ablation, usually scheduled 2–4 weeks later. If your insurer requires a second confirmatory block, it is done on a separate day. A clearly negative block is not repeated.
Call us for fever, a hot or swollen knee, redness or drainage at the sites, or foot weakness that persists beyond the day.
What the evidence shows
Genicular nerve blocks were introduced alongside genicular radiofrequency ablation, and the ablation evidence is the reason the block matters. In the first randomized sham-controlled trial (Choi and colleagues, 2011), patients selected with a positive genicular block had significantly better pain and function at 12 weeks after ablation than after sham. In a larger multicenter trial of cooled genicular RFA versus steroid injection (Davis and colleagues, 2018), 74% of ablation patients had at least 50% relief at 6 months versus 16% after steroid.
The honest caveat is about the block itself. One randomized trial (McCormick and colleagues, 2018) found that patients selected with a genicular block did not have better ablation outcomes than patients who skipped the block, which raises the question of whether the test adds value. Most insurers still require a positive block, some require two, and we use it because a clearly negative block spares a patient an ablation that is unlikely to help. We tell patients that the block is a reasonable screen rather than a perfect predictor.
The block has no meaningful therapeutic effect on its own and contains no steroid; occasional reports of relief lasting days are placebo or coincidence, and insurers do not cover repeated blocks as treatment.
Alternatives and what comes next
A positive block leads to genicular RFA. A negative block, or a patient who prefers injections, points toward knee joint injections with steroid, or toward a surgical opinion about knee replacement. Exercise, weight management and bracing remain the foundation of osteoarthritis care whichever route is chosen. Genicular nerve blocks are performed at our Houston and Webster offices, and in Pearland when that office opens in November 2026.
Safety and preparation
- Blood thinners: a genicular block is a low bleeding-risk procedure and most patients continue their usual medications. Tell us about warfarin, apixaban, rivaroxaban, dabigatran, clopidogrel, ticagrelor, enoxaparin and aspirin; we decide with your prescriber whether any change is needed. Never stop a blood thinner on your own.
- Diabetes: no steroid is used, so blood sugar is not affected. Eat and take your medication normally.
- Infection or fever: we reschedule if you have a fever, a skin problem over the knee, or a hot, swollen joint; a replaced knee with any sign of infection needs the surgeon, not a block.
- Allergies (contrast, steroid, local anesthetic): tell us about reactions to lidocaine, bupivacaine or dental numbing. Contrast is rarely needed; no steroid is used.
- Pregnancy: tell us if you are or could be pregnant; the block can be done with ultrasound instead of X-ray.
- Sedation and driving: no sedation is used, so that the test is accurate. Most people drive themselves home; if you prefer, bring a driver.
- Pain medication on the day: take your usual scheduled medications but no extra or as-needed pain medication the morning of the block or during the 6-hour diary window unless necessary.
- Knee replacement: bring your surgeon's most recent note or X-ray report so we have confirmation that infection and loosening have been excluded.
Risks and side effects
- Soreness or bruising at the three needle sites for 1–2 days
- A patch of skin numbness around the knee for a few hours
- A brief rebound of pain the evening after the anesthetic wears off
- Light-headedness or a vasovagal reaction during the procedure
- Bleeding into the knee or the tissue around it, particularly on blood thinners
- Allergic reaction to local anesthetic
- Temporary numbness or weakness in the lower leg if anesthetic spreads toward the saphenous or peroneal nerve; resolves within hours
- A false-positive or false-negative result
- Infection at the needle site or in the knee joint (a serious concern in a replaced knee; the needles do not enter the joint)
- Injury to the genicular artery with a hematoma
- Injury to the common peroneal nerve with foot drop, avoided by not targeting the inferolateral genicular nerve
- Local anesthetic toxicity if a larger dose enters a blood vessel (very unlikely at these volumes)
Frequently asked questions
What is a genicular nerve block?
It is a diagnostic injection that numbs three small sensory nerves around the knee, the superomedial, superolateral and inferomedial genicular nerves, for a few hours. If your knee pain falls by at least half during that time, those nerves carry the pain and genicular radiofrequency ablation of the same nerves is likely to give months of relief.
How long does a genicular nerve block last?
One to two hours with lidocaine, four to eight hours with bupivacaine. The pain is expected to return the same day; that is part of a positive result. The block contains no steroid and is not a treatment.
What counts as a positive genicular block?
At least 50% relief of your usual knee pain, including with walking, during the anesthetic window. Some insurers require two separate positive blocks. We use a written pain diary for the 6 hours after the injection rather than relying on memory.
Can I have a genicular block if I have had a knee replacement?
Yes. The nerves are targeted on the bone surfaces outside the joint, away from the implant, and the block does not enter the joint. We ask that your surgeon first confirm the replacement is not infected, loose or unstable, since those problems need a different treatment.
Does a genicular nerve block hurt?
There is a brief sting from the skin numbing at three points and pressure as each needle reaches bone. It takes about 10–15 minutes and no sedation is needed. Most patients walk out and drive home.
What happens after a positive genicular block?
We request insurance authorization for genicular radiofrequency ablation, which is usually scheduled 2–4 weeks later. The ablation heats the same three nerves so they stop transmitting pain for typically 6–12 months, and it can be repeated when the nerves regrow.
Sources
- Radiofrequency treatment relieves chronic knee osteoarthritis pain: a double-blind randomized controlled trial (Choi WJ, et al., 2011) (opens in new tab) — Pain
- Cooled Radiofrequency Ablation With Corticosteroid Injection in the Management of Knee Pain From Osteoarthritis (Davis T, et al., 2018) (opens in new tab) — Regional Anesthesia & Pain Medicine
- A Prospective Randomized Trial of Prognostic Genicular Nerve Blocks to Determine the Predictive Value for the Outcome of Cooled Radiofrequency Ablation (McCormick ZL, et al., 2018) (opens in new tab) — Pain Medicine
- Management of Osteoarthritis of the Knee (Non-Arthroplasty): Evidence-Based Clinical Practice Guideline (2021) (opens in new tab) — American Academy of Orthopaedic Surgeons (AAOS)
Next step
Request an appointment
Call (832) 916-2075 or request an appointment online. New patients are welcome; the team confirms insurance and referral requirements before scheduling.